Rotech Healthcare

Author: Rotech Healthcare

What Discharge Teams Should Know Before Sending a Patient Home with NPWT

Sending a patient home with Negative Pressure Wound Therapy (NPWT) takes more than arranging a pump.

For discharge planners, case managers, wound care nurses, WOCNs, home health partners, and referral coordinators, the transition works best when the clinical plan, supply plan, and follow-up plan are clear before the patient leaves the hospital. That includes confirming the order, wound documentation, dressing change responsibility, delivery details, and who the patient or caregiver should contact with questions.

NPWT can be an important part of wound care for appropriately selected patients, but it should be ordered, applied, and managed according to the provider’s clinical judgment, wound type, payer requirements, facility protocols, manufacturer instructions, and follow-up plan. Proper use depends on patient selection, wound preparation, dressing placement, an airtight seal, individualized settings, and trained interdisciplinary care.1


What Should Discharge Teams Confirm Before Sending a Patient Home with NPWT?

Before sending a patient home with NPWT, discharge teams should confirm the provider order, wound documentation, dressing change plan, supply needs, delivery and setup plan, patient and caregiver education, home health or wound clinic follow-up, and troubleshooting contacts.

Teams should also clarify who the patient should call for pump alarms, dressing leaks, supply questions, or wound changes. Coverage and documentation requirements may apply, so referral teams should confirm that the necessary clinical information is complete before discharge.2

Before discharge, confirm:

  • The NPWT order and wound documentation are complete
  • The delivery location and timing are clear
  • Dressing change responsibility is assigned
  • Supplies match the ordered dressing change plan
  • Home health, wound clinic, or provider follow-up is confirmed
  • The patient or caregiver knows who to call for alarms, leaks, wound changes, and supply questions

Healthcare professional discharging a patient while writing on clipboard

Why Home NPWT Discharge Planning Needs More Than an Equipment Order

NPWT is often treated as an equipment task during discharge, but the home transition depends on the handoff around that equipment.

CMS describes NPWT as the application of subatmospheric pressure to a wound to remove exudate and debris. In practical discharge planning terms, that means teams need to account for the full system being sent home, including the suction pump, exudate collection chamber, and dressing sets.4

For patients and caregivers, that means there is more to understand than “a device is coming.” They need to know why the therapy is being used, who will manage dressing changes, what supplies are needed, who is following the wound, and who to contact if something does not seem right.

Without that clarity, common discharge gaps can show up quickly:

  • The pump or supplies are sent to the wrong location
  • Dressing change responsibility is unclear
  • The patient does not know who to call for alarms or leaks
  • Home health or wound clinic follow-up is not confirmed
  • Supply quantities do not match the dressing change plan
  • Documentation is incomplete for coverage or continuation needs
  • Caregivers are unsure how to support the patient at home

For discharge teams, NPWT discharge planning functions as a handoff plan. The goal is to help patients leave with clear instructions, the right supplies, and a follow-up path that does not depend on guesswork once they are home.


Confirm the Wound Documentation and Provider Order

Before discharge, teams should confirm that the NPWT order and wound documentation are complete and aligned with the patient’s care plan.

Coverage and documentation requirements may apply when a patient is discharged with NPWT. CMS outlines NPWT policy requirements through the applicable Local Coverage Determination and related guidance, including the need for wound evaluation, care documentation, and wound measurements by a licensed medical provider. CMS also notes that, before NPWT is applied for covered ulcer or wound categories, the wound therapy program should address general measures such as appropriate dressings, debridement of necrotic tissue when present, and evaluation of nutritional status.3

Because requirements can vary by payer and clinical situation, discharge teams should avoid treating documentation as a last-minute administrative step. At a high level, teams may need to confirm details such as:

  • Current wound measurements
  • Wound location
  • Wound type or diagnosis
  • Current wound notes
  • Prior treatments, when relevant
  • Provider order details
  • Dressing change frequency as ordered
  • Follow-up provider, wound clinic, or home health agency
  • Delivery location and anticipated discharge timing

This is not meant to replace payer guidance, facility policy, or clinical documentation standards. It is a reminder that the discharge plan works best when clinical, documentation, supply, and follow-up details are addressed together.

Medical wound care dressing supplies including gauze and tweezers

Clarify the Dressing Change Plan and Follow-Up Ownership

A patient can leave the hospital with NPWT arranged and still run into confusion at home if no one has clearly explained who is managing dressing changes.

Before discharge, teams should clarify:

  • Who will perform or supervise dressing changes
  • How often dressing changes should occur, based on the provider’s order
  • Which home health agency, wound clinic, or provider is following the patient
  • Who should be contacted for wound changes or clinical concerns
  • Who should be contacted for equipment or supply questions
  • Whether the caregiver has a role in monitoring, organizing supplies, or reporting concerns

Follow-up responsibility should be clear before the patient leaves the hospital. Medicare DME guidance notes that continued NPWT coverage may require regular wound assessment, supervised or directly performed dressing changes, and monthly documentation of wound dimensions and characteristics.3

Patients and caregivers should not have to guess whether to call home health, the wound clinic, the ordering provider, or the equipment provider when questions come up.


Make Sure the Patient and Caregiver Understand the Basics

Patient and caregiver education should be practical, not overwhelming.

Patients do not need to become wound care experts before they go home. They need clear instructions for what the therapy is meant to do, what they should watch for, and who they should contact when questions come up.

At a high level, education should help the patient and caregiver understand:

  • Why NPWT is part of the care plan
  • The importance of keeping the dressing sealed
  • What to do if the pump alarms
  • Who to call for leaks or equipment concerns
  • Who to call for wound changes, fever, increased pain, odor, or drainage concerns
  • How to keep supplies clean, organized, and accessible
  • When and where follow-up care is scheduled

For referral teams, patient education should hold up after discharge, not just during the conversation at bedside. A caregiver who understands who to call for a pump alarm, supply issue, or wound concern is better prepared to respond without unnecessary confusion.

Product delivered in box in front of front door of a house

Plan for Supplies, Delivery, and Resupply Before Discharge

Supply planning can be one of the easiest details to overlook during a busy discharge.

Before the patient leaves, teams should confirm:

  • Delivery location
  • Delivery timing
  • Pump needs
  • Dressing kits
  • Canisters
  • Other ordered supplies
  • Dressing change frequency as ordered
  • Home health or wound clinic involvement
  • Resupply process
  • Contact information for supply questions

Rotech provides wound care supplies, Negative Pressure Wound Therapy solutions, reliable delivery, ordering assistance, and patient/caregiver resources through our Wound Care services.

For patients already using NPWT who need additional supplies, our NPWT Resupply Request page can help start the resupply request process.


Common Home NPWT Challenges to Plan For

Even with a strong discharge plan, questions can come up once the patient is home.

Common home NPWT challenges may include:

  • Pump alarms
  • Dressing seal leaks
  • Confusion about who to call
  • Supplies running low
  • Canister questions
  • Trouble keeping supplies organized
  • Patient or caregiver anxiety
  • Uncertainty about dressing changes
  • Wound changes that need clinical attention

This guidance should not replace facility protocols, manufacturer instructions, home health guidance, or provider instructions. Still, discharge teams can reduce confusion by helping patients understand what is equipment-related, what is wound-related, and who to contact for each.

For example:

  • Pump alarms, supply questions, and delivery concerns may require equipment or DME support.
  • Wound changes, increased pain, fever, drainage changes, odor, bleeding, or other concerning symptoms should be directed to the patient’s healthcare provider or wound care team.
  • Dressing changes should follow the provider’s order and the care team’s instructions.

Clear contact guidance can help patients and caregivers respond more confidently after discharge.

Patient in chair getting discharged from hospital

How Rotech Supports NPWT Transitions from Hospital to Home

At Rotech, we help referral teams coordinate wound care needs so patients and caregivers have a clearer path after discharge.

Our wound care services include:

  • Negative Pressure Wound Therapy solutions
  • Wound care supplies and advanced dressings
  • Dressing and supply coordination
  • Delivery support
  • Ordering assistance
  • Patient and caregiver resources

Our Wound Care Resources page also includes patient and caregiver education related to wound care basics, pressure ulcers, sores that will not heal, debridement, infection, diabetic foot ulcers, skin health, and NPWT resources.

For discharge teams, our role is to help reduce avoidable friction around equipment, supplies, delivery, and patient education. We work to help patients and caregivers feel less uncertain as they transition from hospital-based care to wound care at home.

You can also explore our broader Products & Services to learn more about respiratory and home medical support available through Rotech.


Frequently Asked Questions

What should be confirmed before a patient goes home with NPWT?

Before discharge, teams should confirm the provider order, wound documentation, delivery location, dressing change plan, supply needs, follow-up provider or agency, and patient/caregiver education. Coverage and documentation requirements may apply, and CMS outlines NPWT-related policy requirements through its provider compliance guidance and Local Coverage Determination resources.

Who is responsible for NPWT dressing changes after discharge?

Responsibility depends on the patient’s care plan, provider order, payer requirements, and whether home health, a wound clinic, or another licensed professional is involved. Medicare DME guidance notes that continued NPWT coverage may require regular wound assessment, supervised or directly performed dressing changes, and monthly documentation of wound dimensions and characteristics.

What NPWT supplies may need to be coordinated before discharge?

NPWT supply needs may include the pump, dressing sets or kits, canisters, and other supplies ordered for the patient’s wound care plan.

What common issues can patients or caregivers face with NPWT at home?

Patients and caregivers may have questions about pump alarms, dressing leaks, supply organization, canisters, dressing change timing, resupply, or who to call with concerns. Discharge teams can help by providing clear contact information for clinical concerns, equipment questions, and supply needs before the patient leaves.

How can a DME or wound care partner support NPWT transitions?

A DME or wound care partner can help coordinate NPWT solutions, wound care supplies, delivery, ordering assistance, and patient/caregiver resources. Through our wound care services, Rotech provides Negative Pressure Wound Therapy solutions, wound care supplies, reliable delivery, and patient/caregiver support.


Coordinate NPWT Support Before Discharge

A strong NPWT discharge plan gives patients and caregivers more than a device. It gives them clear next steps, the right supplies, a follow-up plan, and contact information for questions after they leave the hospital.

If your team is coordinating NPWT discharge planning, our team can help with wound care supplies, NPWT solutions, delivery coordination, ordering assistance, and patient/caregiver resources.


References

  1. Zaver, V., & Kankanalu, P. (2023). Negative Pressure Wound Therapy. PubMed; StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK576388/
  2. Centers for Medicare & Medicaid Services (CMS). (2025). Billing and Coding: Wound and Ulcer Care (A58565). Cms.gov. https://www.cms.gov/medicare-coverage-database/view/article.aspx?articleId=58567&ver=29
  3. Centers for Medicare & Medicaid Services (CMS). (2023). LCD – Negative Pressure Wound Therapy Pumps (L33821). Cms.gov. https://www.cms.gov/medicare-coverage-database/view/lcd.aspx?lcdid=33821&ver=28&keyword=wound&keywordType=starts&areaId=s12&docType=NCA
  4. Centers for Medicare & Medicaid Services (CMS). (2024). Negative Pressure Wound Therapy | CMS. Cms.gov. https://www.cms.gov/training-education/medicare-learning-networkr-mln/compliance/medicare-provider-compliance-tips/negative-pressure-wound-therapy

When a Wound Won’t Heal: What Patients and Caregivers Should Know

A wound can start small and still become stressful when it does not seem to be getting better.

Maybe a sore has been slow to close. A wound has more drainage than usual. Or maybe you are helping a parent, spouse, or loved one keep track of dressing changes, supplies, and instructions from several providers.

Wound care at home can feel like a lot to manage, especially when you are not sure what changes are expected and what should be reported. The most important step is to follow your healthcare provider’s wound care plan and ask questions when something does not seem right.

With the right instructions, wound care supplies at home, and support, patients and caregivers can feel more prepared to manage daily wound care routines.


When Should You Ask for More Help with a Wound?

Contact your healthcare provider if a wound is not improving, becomes more painful, has more redness or swelling, has increased drainage or odor, or if you notice fever or other concerning symptoms.

You should also ask for help if you are unsure how to use wound care supplies, if supplies are running low, or if dressing changes are becoming difficult to manage at home. The right wound care supplies and support can help you follow your provider’s care plan more consistently.

Person getting wound dressed by healthcare professional on their arm

Why Some Wounds Take Longer to Heal

Not every wound heals at the same pace. Some wounds may take longer because of where they are on the body, how much pressure is placed on the area, how much drainage is present, or whether another health condition affects healing.

A wound may also need more support if the skin is fragile, if circulation is poor, or if the person has diabetes or limited mobility. For caregivers, it can be helpful to keep notes about how the wound looks, how often supplies are being changed, and whether anything seems different from day to day.

Your healthcare provider can help determine why a wound is healing slowly and whether the care plan needs to change.


Signs a Wound May Need Medical Attention

Some wound changes should be shared with a healthcare provider promptly. Do not try to diagnose the problem yourself, but do pay attention to changes.

Contact your provider if you notice:

  • More redness, warmth, or swelling around the wound
  • Increased pain or tenderness
  • More drainage than usual
  • Drainage that changes color or has an odor
  • A wound that appears larger or deeper
  • Skin around the wound that becomes darker, fragile, or irritated
  • Fever or chills
  • A wound that is not improving as expected
  • Supplies that are not working well or are difficult to use
  • Any change that feels concerning or unusual

If symptoms feel severe or urgent, seek emergency medical care.

Healthcare professional dressing a person's wound on their foot

Common Types of Wounds That May Need Extra Support

Some wounds are more likely to need ongoing care, specific supplies, or additional support at home.

These may include:

  • Pressure sores or pressure ulcers: These can develop when pressure stays on one area of the body for too long, especially for people who sit or lie in one position for extended periods.
  • Diabetic foot ulcers: People with diabetes may be at higher risk for wounds on the feet, especially if they have changes in feeling, circulation, or skin health.
  • Wounds with heavy drainage: Some wounds require dressings that can help manage moisture and protect surrounding skin.
  • Surgical wounds: Some surgical wounds need continued dressing changes or monitoring after a patient returns home.
  • Burns or skin grafts: These wounds may require specific care instructions and supplies.
  • Slow-healing wounds: A wound that does not seem to improve may need more attention from a healthcare provider.

No matter the wound type, always follow your provider’s instructions for cleaning, dressing changes, and activity limits.


Wound Care Supplies That May Be Used at Home

Wound care supplies at home can vary depending on the wound, the amount of drainage, the provider’s instructions, and the patient’s overall care plan.

Supplies may include:

It is important to use supplies as directed. A dressing that works well for one wound may not be right for another. If a dressing is not staying in place, drainage is leaking through, or you are unsure whether you have the right supplies, contact your healthcare provider or wound care team.

If you need help understanding available wound care products and support, you can learn more about our wound care supplies and services.

What Is Negative Pressure Wound Therapy?

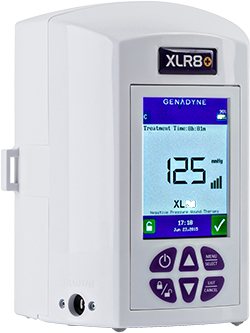
Genadyne XLR8 NPWT Pump

Negative Pressure Wound Therapy, often called NPWT, is a wound treatment that may be prescribed for certain types of wounds.

In general terms, NPWT uses a sealed dressing and a pump to create gentle negative pressure around the wound. This type of therapy may be used for certain wounds that need additional support, such as wounds with significant drainage, diabetic ulcers, burns, skin grafts, or wounds that are slow to heal.

NPWT is not something patients should start on their own. It should be ordered and managed under the direction of a healthcare provider. If NPWT is part of your care plan, make sure you understand:

  • How the device should be used
  • How often dressings should be changed
  • What supplies you need to keep on hand
  • Who to call if the pump alarms
  • What changes should be reported to your provider

If you already use NPWT and need additional supplies, our NPWT Resupply Request page can help you start the request process.


How Caregivers Can Help with Wound Care Routines

Caregivers often play an important role in helping wound care stay organized at home. You do not need to have all the answers, but it helps to have a clear system.

Caregivers can help by:

  • Keeping wound care supplies in one clean, easy-to-find place
  • Following the provider’s dressing change instructions
  • Writing down when dressings are changed
  • Watching for changes in pain, drainage, odor, redness, or swelling
  • Making sure supplies are reordered before they run low
  • Keeping provider and supply contact information nearby
  • Asking questions when instructions are unclear
  • Helping the patient keep follow-up appointments

It may also be helpful to take notes during appointments, especially if more than one person helps with care. A simple notebook or phone note can make it easier to track instructions, supply needs, and questions for the next visit.

Senior woman drinking water at table in her kitchen

Nutrition, Hydration, and Wound Healing Support

Food and fluid intake can play a role in overall health and healing, but every patient’s needs are different.

If you are managing a slow-healing wound, ask your healthcare provider whether nutrition or hydration guidance should be part of your care plan. This is especially important for patients with diabetes, kidney disease, heart failure, swallowing concerns, or other medical conditions that may affect diet recommendations.

Caregivers should avoid making major diet or supplement changes without checking with the healthcare provider first.


What About Debridement?

Some wounds may need help removing unhealthy or dead tissue so healing can continue. This process is called debridement.

Debridement should be done or directed by a qualified healthcare professional. If your provider mentions debridement, ask what to expect, how the wound should be cared for afterward, and what supplies you may need at home.

Do not try to remove tissue from a wound unless your healthcare provider has specifically instructed you to do so.

Healthcare professional wrapping blue gauze around a woman's forearm

How Rotech Supports Wound Care at Home

At Rotech, our goal is to help patients and caregivers feel more supported while managing wound care at home.

We provide wound care supplies, advanced dressing options, Negative Pressure Wound Therapy solutions, delivery support, ordering support, and wound care resources for patients and caregivers. Our team can also help with supply questions and connect you with the appropriate local resource when you need support.

You can also visit our Wound Care Resources page for patient and caregiver information, including resources on skin health, pressure ulcers, sores that will not heal, infection, diabetic foot ulcers, debridement, and wound care basics.


Frequently Asked Questions

What are signs a wound needs medical attention?

Contact your healthcare provider if a wound is not improving, becomes more painful, has more redness or swelling, has increased drainage or odor, or if you notice fever, chills, or other concerning symptoms. If symptoms feel severe or urgent, seek emergency medical care.

Why is my wound taking so long to heal?

A wound may take longer to heal for many reasons, including pressure on the area, drainage, circulation problems, diabetes, infection concerns, nutrition needs, or other health conditions. Your healthcare provider can help determine what may be affecting healing and whether your care plan needs to change.

What wound care supplies might be used at home?

Wound care supplies may include gauze, tape, wraps, dressings, hydrogels, gelling fibers, hydrocolloids, or Negative Pressure Wound Therapy supplies if prescribed. The right supplies depend on the wound and your provider’s instructions.

What is Negative Pressure Wound Therapy?

Negative Pressure Wound Therapy, or NPWT, is a treatment that may be prescribed for certain wounds. It uses a sealed dressing and a pump to create negative pressure around the wound. If NPWT is part of your care plan, your healthcare provider or wound care team should explain how to use it, when to change supplies, and who to call with questions.

How can caregivers help with wound care at home?

Caregivers can help by keeping supplies organized, following dressing change instructions, tracking wound changes, reordering supplies before they run low, and knowing when to call the healthcare provider. Caregivers should also ask questions when instructions are unclear.


Get Support for Wound Care Supplies

Managing wound care at home is easier when you have clear instructions, the right supplies, and a support team you know how to reach.

If you or a loved one needs help with wound care supplies, NPWT support, or local wound care resources, our team can help guide you to the right place.

Building a Better Discharge Experience for Patients with Multiple Comorbidities

A patient hospitalized with COPD rarely has only COPD.

Heart failure, obstructive sleep apnea, diabetes, obesity, limited mobility, or a healing wound may also be part of the clinical picture, along with multiple medications, specialists, caregivers, and equipment needs waiting at home.

Each condition may have its own treatment plan. Together, they create a discharge process that depends on clear coordination across therapies, documentation, education, insurance requirements, and follow-up.

For hospital teams, every additional diagnosis can add another referral, another equipment need, another teaching point, and another opportunity for communication to break down.

A strong discharge process helps the patient leave the hospital with the equipment, instructions, support, and continuity needed to keep the care plan moving at home.


What Makes Discharge Easier for Patients with Multiple Comorbidities?

Patients with multiple chronic conditions often leave the hospital with several therapies that need to begin or continue right away.

Effective discharge planning starts before the patient leaves the acute-care setting. That may include coordinating equipment delivery, patient and caregiver education, documentation, insurance verification, and follow-up support.

When these elements are aligned, patients and caregivers are better prepared to continue the treatment plan established by the care team.

Female doctor reviewing information with female senior patient

Why Multiple Comorbidities Create More Complex Discharges

Every discharge includes logistics. Complex discharges add more layers to coordinate.

Consider a patient admitted for a COPD exacerbation who also has heart failure, obesity, diabetes, and obstructive sleep apnea. Before discharge, the care team may need to coordinate:

Each task may be manageable on its own. Coordinating all of them within a short discharge timeline is where referral teams often feel the most pressure.

The more therapies involved, the more important it becomes to reduce handoffs, clarify responsibilities, and confirm that patients know what to do once they get home.


Common Challenges During Complex Discharges

While every patient is different, discharge teams often encounter similar barriers when planning for medically complex patients.

Multiple Equipment Needs

Patients may require oxygen therapy, PAP therapy, mobility equipment, nebulizers, wound care supplies, or diabetes supplies at the same time. When multiple vendors are involved, referral teams may have to manage separate communication channels, delivery timelines, documentation requests, and follow-up processes.

Insurance and Authorization Requirements

Coverage requirements can vary by therapy and payer. Documentation, authorization, and benefit verification may all affect how quickly equipment or supplies can be arranged.

Patient and Caregiver Education

Learning one new therapy can be challenging. Learning several at once can be overwhelming.

Patients and caregivers need clear, practical education that explains:

  • How each piece of equipment works
  • When and how each therapy should be used

  • Who to call with equipment or supply questions

  • What changes should be shared with the prescribing provider
  • How each therapy fits into the broader care plan

Communication Across Providers

Primary care physicians, pulmonologists, cardiologists, respiratory therapists, home health clinicians, case managers, discharge planners, and DME providers may all play a role in the transition home.

Without clear communication pathways, important details can become fragmented between the hospital and the home setting.

Healthcare professional typing at keyword

A Practical Check Before Discharge

For patients with several home therapy needs, referral teams may be able to reduce confusion by confirming a few key details before the patient leaves the hospital:

  • Has each ordered therapy been matched with the correct equipment or supply need?
  • Has documentation been sent to the appropriate provider or supplier?
  • Have insurance or authorization requirements been reviewed?
  • Does the patient or caregiver know when equipment will arrive?
  • Does the patient know who to call for equipment questions?
  • Does the patient know which symptoms or changes should be reported to the prescribing provider?
  • Has follow-up support been clearly explained?

These steps may seem simple, but they can make a meaningful difference when patients are managing several therapies at once.


Why One Connected DME Partner Can Simplify the Process

For patients with multiple comorbidities, equipment is only one part of the discharge plan. The larger challenge is coordinating the details around that equipment.

Working with a DME partner that supports multiple therapy areas can help referral teams reduce unnecessary complexity by:

  • Streamlining referral communication
  • Coordinating equipment setup and delivery
  • Helping manage documentation and insurance requirements
  • Providing consistent patient and caregiver education
  • Offering one point of contact for multiple home therapy needs
  • Supporting patients after discharge with service and supply needs

Instead of coordinating several separate vendors, referral teams may be able to simplify the transition through one connected relationship.

That can create a more consistent experience for providers, caregivers, and patients.

Related: What Makes a Successful Home NIV Transition? A Practical Guide for Discharge Teams

Oxygen tank and mask

The Role of Respiratory Support, Equipment Setup, and Patient Education

For patients with multiple comorbidities, equipment needs are rarely limited to one therapy.

A patient discharged after a COPD exacerbation may need home oxygen therapy while also using PAP therapy for obstructive sleep apnea. Another patient may be transitioning home with non-invasive ventilation, diabetes management supplies, mobility equipment, or wound care solutions.

Providing the right equipment is an important first step. Patients and caregivers also need to understand how to use it safely and consistently at home.

That includes education on:

  • When and how each therapy should be used
  • Basic equipment setup and maintenance
  • Common troubleshooting steps
  • Supply replacement or reorder processes
  • When to contact the prescribing provider
  • Who to call with equipment or service questions

When education is rushed or divided among several organizations, important details can be missed. Consistent instruction at setup can help patients and caregivers feel more prepared as they move from hospital routines to home routines.

For referral teams, working with a partner that supports multiple therapy areas can help create a more coordinated experience from the start.

Make the Next Complex Discharge Easier

When patients require multiple therapies, coordinated support can reduce unnecessary handoffs and help them transition home with greater confidence.


Why Follow-Up Matters After the Patient Goes Home

Discharge is a milestone, but it is not the end of the care transition.

The first days at home often determine whether patients and caregivers can establish new routines or begin running into barriers. Equipment questions come up. Supplies may need to be replaced. Instructions may need to be reinforced. Caregivers may discover challenges that were not obvious in the hospital.

Without timely support, small issues can lead to therapy interruptions, missed follow-up steps, or avoidable frustration for patients and caregivers.

That is why effective discharge planning extends beyond the day the patient leaves the hospital.

A coordinated post-acute partner can help reinforce education, address equipment concerns, communicate with referral sources when appropriate, and support patients as they continue the prescribed care plan at home.

Woman sitting at home on bed with oxygen tank near her

How Rotech Helps Referral Teams Support Complex Discharges

Hospital teams are balancing discharge efficiency, patient experience, documentation requirements, and continuity of care. Rotech’s role is to help simplify what happens after the referral is placed.

Across respiratory care, sleep therapy, diabetes management, wound care, mobility, and home medical equipment, our team works alongside referral sources to help coordinate the details that keep care moving forward.

Depending on the patient’s needs, provider orders, payer requirements, and local availability, Rotech may help with:

  • Coordinating equipment setup and delivery
  • Assisting with documentation and insurance verification
  • Educating patients and caregivers during equipment setup
  • Supporting multiple therapy needs through one organization whenever possible
  • Communicating with referral teams throughout the transition
  • Providing ongoing service and supply support after discharge

For medically complex patients, fewer handoffs can help create a smoother experience for both providers and the people they care for.

Our goal? Helping referral teams support patients as they continue prescribed care safely and confidently at home.


Coordinated Support Through CarePLUS™

Rotech’s CarePLUS™ approach is designed to support healthcare professionals by serving as an extension of the care team in the home.

Through CarePLUS™, Rotech helps coordinate services with prescribed orders, identify potential patient needs, share relevant updates with providers, and support patients as they manage care at home.

For complex discharges, that added visibility can be especially valuable. Patients with multiple comorbidities may need more than equipment delivery. They may need reinforcement, practical education, ongoing service, and a clear path for questions after they leave the hospital.

Healthcare professional writing on clipboard with pen

Frequently Asked Questions

What makes discharge planning more challenging for patients with multiple comorbidities?

Patients with multiple chronic conditions often require several therapies, specialists, medications, supplies, and pieces of equipment at the same time. Coordinating documentation, insurance requirements, equipment delivery, patient education, and follow-up across multiple services can increase the complexity of discharge planning.

How can a DME partner support complex patient discharges?

A home medical equipment partner can help coordinate equipment delivery, assist with documentation and insurance requirements, provide patient and caregiver education, support multiple therapy needs, and communicate with referral sources during the transition home. Working with one organization that supports several therapy areas may also help reduce unnecessary handoffs.

Why is patient education important before discharge?

Patients are often expected to begin or continue therapies soon after returning home. Clear education helps patients and caregivers understand how equipment works, when to use it, who to contact with questions, and how each therapy supports the care plan prescribed by their healthcare provider.

What types of respiratory equipment may be involved in complex discharges?

Depending on the patient’s diagnosis and provider orders, discharge plans may include home oxygen therapy, CPAP or BiLevel therapy, non-invasive ventilation, nebulizers, airway clearance devices, pulse oximetry, and related respiratory supplies.

How can providers help reduce confusion after a patient goes home?

Providers can help by starting discharge planning early, confirming equipment timelines, identifying a primary contact for questions, reinforcing patient and caregiver education, and partnering with organizations that provide coordinated post-discharge support.


Make the Next Complex Discharge Easier

Patients with multiple comorbidities rarely fit into one diagnosis or one therapy. Successful discharge planning reflects that reality by coordinating the people, equipment, education, and follow-up needed to support the patient at home.

At Rotech Healthcare, we work alongside referral teams to help simplify that process through coordinated home medical equipment, respiratory support, patient education, and ongoing service.

Whether a patient is transitioning home with oxygen therapy, sleep therapy, diabetes supplies, wound care, mobility equipment, or several therapies together, our team helps make the next step easier to manage.

Coordinating Care at Home with Multiple Chronic Conditions

Managing more than one health condition often means managing more than one routine.

Maybe you use oxygen during the day, a CPAP machine at night, diabetes supplies before meals, and mobility equipment to move safely around the house. Maybe you are helping a parent keep track of supplies, appointments, insurance updates, and instructions from several different providers.

That is a lot to organize, but with the right plan and support, home care can feel more manageable.

Having the right equipment, clear routines, and dependable support can help connect the pieces, so daily care feels easier to follow.


How Can Home Care Be Easier with Multiple Chronic Conditions?

Home care is easier when your equipment, supplies, and support all work together around your care plan.

That means knowing what each device is for, when supplies need to be replaced, who to call with questions, and how to spot changes that should be shared with your healthcare provider.

The goal is to create a routine that helps you stay consistent, informed, and supported at home.

Male doctor speaking to male patient while reviewing clipboard

Why Managing More Than One Condition Can Feel Complicated

Many people living with chronic conditions do not have just one diagnosis or one piece of equipment. For example, someone with COPD may also have sleep apnea, diabetes, heart failure, mobility needs, or a wound that requires ongoing care.

That can mean:

  • Multiple doctors or specialists
  • More than one home medical device
  • Different supply replacement schedules
  • Insurance updates or benefit changes
  • Medication and therapy routines
  • Caregiver coordination
  • Questions about who to call when something changes

Even small details can become stressful if they are not organized. Running low on CPAP supplies, missing a diabetes supply reorder, forgetting who handles oxygen equipment, or being unsure about wound care instructions can interrupt the routine you rely on.


Start With One Clear List of Your Therapies, Supplies, and Care Contacts

One of the simplest ways to make home care easier is to keep one current list of everything you use and who supports it.

Your list may include:

  • Oxygen equipment, including concentrators, tanks, tubing, or cannulas
  • CPAP or BiLevel equipment, including masks, filters, tubing, and cushions
  • Diabetes supplies, such as CGMs, meters, test strips, lancets, or insulin pump supplies
  • Wound care supplies or therapy equipment
  • Nebulizers or airway clearance devices
  • Mobility equipment, such as walkers, wheelchairs, canes, or hospital beds
  • Provider names and phone numbers
  • Your local Rotech location or support contact information
  • Insurance information and effective dates

Keep this list somewhere easy to find. Caregivers may also want a copy, especially if they help with appointments, supply orders, or daily routines.

Man bent over with hands on knees because he is short of breath

Know Which Symptoms or Changes Should Be Shared with Your Care Team

Your home equipment and supplies are there to support your prescribed care plan. If something changes, it is important to know when to ask for help.

Contact your healthcare provider if you notice new or worsening symptoms, such as:

  • Increased shortness of breath
  • Chest pain or pressure
  • New dizziness, confusion, or extreme fatigue
  • Changes in wound appearance, drainage, odor, or pain
  • Low or high blood sugar readings outside your provider’s guidance
  • New swelling or sudden weight changes
  • Trouble using equipment as prescribed
  • Any symptom that feels unusual or concerning

If you are having a medical emergency, call 911.

You should also contact your home medical equipment provider if equipment is not working properly, supplies are missing, or you are unsure how to use or maintain something.


Make Equipment and Supply Routines Easier to Manage

When several therapies are part of daily life, small routines can prevent bigger headaches.

Try these tips:

  • Set reorder reminders. Add supply replacement dates to your calendar.
  • Keep backup supplies when possible. Ask your provider what extras are appropriate to keep on hand.
  • Store supplies in one place. Use labeled bins or shelves for CPAP, oxygen, wound, or diabetes items.
  • Check equipment regularly. Look for cracked tubing, loose connections, dirty filters, or worn mask cushions.
  • Review instructions after setup. If something feels unclear, ask questions before it becomes frustrating.
  • Update insurance information promptly. Plan changes can affect supply coverage, billing, or provider networks.
  • Tell your care team about changes. New symptoms, new equipment needs, or changes in your home setup may affect your care plan.

If you use CPAP supplies, Sleep Central can help make replacement supplies easier to manage. If you need support with oxygen, diabetes supplies, wound care, or other equipment, your local Rotech team can help guide you to the right resource.

Female doctor speaking to senior woman while looking at tablet together

How Coordinated Support Can Help Connect the Pieces

Coordinated support means you are not trying to manage every detail on your own.

For patients with multiple care needs, support may include:

  • Helping verify equipment or supply needs
  • Explaining how equipment works at home
  • Coordinating supply delivery
  • Helping with insurance or documentation questions
  • Supporting caregiver education
  • Connecting patients with the right local contact
  • Helping identify when equipment needs may have changed

Rotech’s CarePLUS™ approach is one way coordinated support can make things easier at home. Through CarePLUS™, our team helps keep an eye on how things are going and supports you between visits with your healthcare provider.

That might include noticing when something feels off, helping you understand your equipment, coordinating certain tests when ordered, or making sure important updates are shared with your provider so your care stays on track.


How Rotech Supports Patients with Multiple Care Needs at Home

Rotech provides respiratory and home medical products and services designed to help patients manage care at home with more confidence.

Depending on your needs and your provider’s orders, our services may include:

Our team understands that equipment should support your life at home, not make it harder. We help patients and caregivers learn how to use equipment, understand supply routines, and know where to turn with questions.


Related Reading

You may also find these resources helpful:

View of senior man's hands typing on laptop with his tablet and glasses next to him

Frequently Asked Questions

How do I keep track of multiple home medical supplies?

Start with a simple list of the supplies you use, how often they are replaced, who provides them, and when you should reorder. Many patients and caregivers find it helpful to keep this list near their medication list or calendar. If your supplies come from more than one source, write down each contact number so you know who to call.

Can one home medical equipment provider help with more than one therapy?

In many cases, yes. A home medical equipment provider may support several types of equipment or supplies, such as oxygen therapy, CPAP supplies, diabetes supplies, wound care solutions, nebulizers, or mobility equipment. Your exact services depend on your physician’s orders, insurance coverage, and local availability.

What should I do if my equipment needs change?

If your symptoms change or you think your equipment is no longer meeting your needs, contact your healthcare provider first. Your doctor can determine whether your care plan or equipment order needs to be updated. You can also contact your Rotech team if equipment is not working properly, supplies are missing, or you have questions about setup or maintenance.

How can caregivers help coordinate care at home?

Caregivers can help by keeping supply lists updated, tracking appointments, saving important phone numbers, watching for changes in symptoms, and helping the patient follow equipment instructions. Caregivers should also know when to call the doctor, when to call the equipment provider, and when to seek emergency care.

When should I contact my doctor about new or worsening symptoms?

Contact your healthcare provider if you notice new or worsening symptoms, changes in breathing, changes in wound appearance, unusual blood sugar readings, new swelling, dizziness, extreme fatigue, or trouble following your prescribed care plan. If symptoms are severe or feel like an emergency, call 911.


Get Support for Your Home Medical Equipment Needs

Managing multiple conditions at home is easier when your equipment, supplies, and support are connected around your care plan.

Rotech is here to help you feel more confident with your home medical equipment needs, from setup and education to ongoing support and supply coordination.

ALS Home Ventilation: What Hospital Discharge Teams Should Expect from a DME Partner 

Discharging a patient with amyotrophic lateral sclerosis (ALS) and respiratory involvement is not a routine transition.

In most post-acute scenarios, patients stabilize, receive equipment, and gradually return toward baseline. ALS follows a different path. Patients go home with a progressive condition, increasing respiratory needs, and caregivers who must quickly learn to manage complex ventilation support in real time.

For hospital teams, this moment carries weight. It marks a critical transition in the care journey, where the quality of support at home can significantly influence outcomes.

Respiratory failure remains the leading cause of death in ALS, and the transition from hospital to home is a key inflection point. Early, well-coordinated ventilation support can improve both quality of life and survival, while delayed or poorly managed noninvasive ventilation (NIV) is associated with worse outcomes.1

For discharge planners, case managers, and ALS clinics, choosing a DME partner is not simply operational. It is a clinical decision that shapes what happens next.


Why ALS Requires a Different Post-Acute Approach

ALS is a progressive neurodegenerative disease that affects both upper and lower motor neurons. Respiratory muscle weakness is not a late-stage issue, rather it is central to the disease from early on.

Most patients will require noninvasive ventilation (NIV) during the course of their disease, often earlier than traditional thresholds suggest.

  • Declines in inspiratory strength may occur before FVC drops below 50%
  • Waiting for traditional thresholds may delay therapy initiation2

Unlike other respiratory populations:

  • ALS patients do not stabilize after discharge
  • They progress into greater dependence on ventilation
  • Their needs require continuous reassessment and adjustment

This creates a fundamentally different care model, one that standard DME approaches are not designed to support.


Healthcare professional in scrubs writing on clipboard and smiling

How ALS Care Differs from Standard DME Models

ALS respiratory care requires a longitudinal, clinically integrated approach, not a transactional one.

Dimension Standard Post‑Acute DME ALS Respiratory Care
Timeline Weeks to months; patient stabilizes or recovers Months to years; patient progresses into greater dependence
Equipment trajectory Static or decreasing needs over time Escalating needs; settings and interfaces require ongoing adjustment
Reassessment frequency Periodic or as‑needed Continuous; respiratory status changes unpredictably
Caregiver involvement Variable; often supplemental Central; caregivers manage daily therapy and troubleshooting
Clinical coordination Primarily with referring physician Multidisciplinary coordination across neurology, pulmonology, respiratory therapy, palliative care, and community services
DME relationship model Transactional; equipment delivery and periodic resupply Longitudinal; ongoing clinical relationship with proactive support

This distinction directly shapes what patients, caregivers, and clinical teams need from a home medical equipment partner.


Ventilation in ALS: More Than Supplying a Device

Noninvasive ventilation (NIV) has been shown to improve survival and quality of life in ALS patients with respiratory insufficiency.3

But outcomes depend on how therapy is implemented, not just whether it is prescribed.

Effective ALS ventilation requires:

  • proper patient acclimation
  • interface optimization
  • ongoing setting adjustments
  • early troubleshooting of tolerance issues

Common barriers include:

  • mask discomfort
  • air leaks
  • pressure intolerance
  • disrupted sleep

Without early intervention, patients may abandon therapy.

Education is equally critical. Patients and caregivers must understand:

  • how the equipment works
  • what to expect during adaptation
  • when to seek help

Studies show adherence improves significantly with structured education and ongoing support.4


Man pushing another man who is in a wheelchair while they are outside

The Caregiver Factor in ALS Ventilation

Caregivers are central to ALS respiratory care.

They manage:

  • daily ventilation therapy
  • equipment troubleshooting
  • nighttime monitoring
  • escalation of concerns

Research shows caregiver burden increases significantly once ventilation is required, with some providing up to 14 hours of care per day.5

Such demands lead nearly 30% of caregivers to report that their own quality of life is worse than the patient’s.5 Caregiver strain directly impacts patient outcomes, in addition to quality of life. Supporting caregivers is a core component of effective ALS care.


What Hospitals Should Expect from a DME Partner

Not all DME providers are equipped to support ALS patients. Hospital teams should look for partners with capabilities aligned to the complexity of the disease.

1. Disease-Specific Clinical Expertise

DME partner should have respiratory therapists and clinicians with direct experience managing neuromuscular disease — staff who understand the progression trajectory, the interface challenges, and the need for ongoing adjustment.

2. A Single Point of Contact for Coordination

The DME partner should provide a dedicated contact, so someone who knows the patient, can liaise with the ALS clinic and pulmonology team, and can expedite responses when needs change.

3. Capacity for Longitudinal Support

The partner should have systems in place for ongoing monitoring, periodic reassessment, and proactive outreach, not just reactive service when patients call with problems.

4. Responsiveness to Changing Needs

When a patient’s respiratory status declines, the DME partner must be able to respond quickly, adjusting settings, changing interfaces, or escalating support without lengthy approval delays.

5. Comfort Managing Complex Ventilator Therapy

This includes not just standard bilevel devices, but portable home ventilators, volume-targeted modes, and coordination with airway clearance strategies. The partner should be able to manage the full spectrum of respiratory support that ALS patients may eventually require.

6. Caregiver Education and Support

Caregivers are the frontline of home ventilation in ALS. The DME partner should provide structured training, accessible resources, and ongoing availability for questions and troubleshooting.


Physical therapist assisting mature woman with using a spirometer to improve the functioning of lungs.

Inside Rotech’s ALS Ventilation Program

Rotech Healthcare’s ALS Ventilation Program is designed to support patients, caregivers, and clinical teams throughout the progression of the disease. The program functions as an extension of the care team in the home.

Key features include:

  • Individualized plans of care tailored to disease stage and patient needs
  • Dedicated Ventilator Patient Specialist serving as a single point of contact
  • Patient and caregiver education for confidence and adherence
  • Ongoing in-home visits and follow-up
  • Coordination with ALS clinics and physicians
  • Continuous titration of settings per physician orders
  • Spirometry and FVC monitoring
  • Portable ventilators to support mobility and independence
  • Backup ventilator options when appropriate
  • 24/7 clinical support for real-time troubleshooting

This model supports both clinical continuity and patient stability outside the hospital.


Key Takeaways for Discharge Teams

For hospital teams managing ALS patients with respiratory involvement:

  • Engage DME partners early
    Ideally at the time of NIV consideration, not during crisis
  • Prioritize ALS-specific expertise
    Not all respiratory providers have neuromuscular experience
  • Ensure clear communication pathways
    Coordination gaps create care gaps
  • Assess caregiver readiness
    Education and support reduce downstream complications
  • Plan for progression
    ALS care is long-term — choose partners who can adapt over time

Frequently Asked Questions About NIV

Why is ALS ventilation different from COPD?

ALS involves progressive muscle weakness, requiring continuous adjustment and caregiver involvement.

When should ALS patients start noninvasive ventilation?

Earlier initiation may improve outcomes. Waiting for traditional thresholds like FVC <50% may delay benefit.2

How often should ventilator settings be adjusted?

Regular reassessment is expected as respiratory function declines.

Why is caregiver support critical?

Caregivers manage daily therapy. Their ability to do so directly impacts adherence and outcomes.


Healthcare professional smiling at patient

Conclusion

ALS post-acute care, particularly for patients with respiratory involvement, requires a different approach than standard DME models provide.

The progressive nature of the disease, the centrality of respiratory support, the burden on caregivers, and the need for ongoing coordination all demand partners who understand ALS as a long-term clinical relationship, not a one-time equipment delivery.

For hospital teams and ALS clinics, the choice of DME partner is a meaningful clinical decision. The right partnership reduces friction, supports patients through transitions, and aligns post-acute care with the goals established by the care team.

Rotech’s ALS Ventilation Program was built with these principles in mind, not as a product, but as a model of care designed to extend the reach of clinical teams into the home setting where ALS patients spend most of their lives.

Learn More About Rotech’s ALS Program


References

  1. Zimnoch, M., Eldeiry, D., Oluwabunmi Aruleba, Schwartz, J., Avaricio, M., Ishikawa, O., Mina, B., & Esquinas, A. (2025). Non-Invasive Ventilation: When, Where, How to Start, and How to Stop. Journal of Clinical Medicine, 14(14), 5033–5033. https://doi.org/10.3390/jcm14145033
  2. Jimenez, J. V., Tang, M. J., Wilson, M. W., Morrison, A. H., Ackrivo, J., & Choi, P. J. (2024). Initiation of noninvasive ventilation in patients with amyotrophic lateral sclerosis. Muscle & Nerve, 70(5), 1099–1103. https://doi.org/10.1002/mus.28250
  3. Sancho, J., Ferrer, S., & Signes-Costa, J. (2025). Noninvasive Ventilation Effectiveness in Amyotrophic Lateral Sclerosis. Journal of Clinical Medicine, 14(23), 8609. https://doi.org/10.3390/jcm14238609
  4. Sau, D., Li, P. W.-C., Lau, J. C.-C., Alice, S., Ip, M., Linda, L., Chung, H., & Iris, K. (2024). Health Communication and Adherence to Noninvasive Ventilation in Chronic Hypercapnic Respiratory Failure. JAMA Network Open, 7(12), e2451614–e2451614. https://doi.org/10.1001/jamanetworkopen.2024.51614
  5. Tang, S., Li, L., Xue, H., Cao, S., Li, C., Han, K., & Wang, B. (2021). Caregiver burden and associated factors among primary caregivers of patients with ALS in home care: a cross-sectional survey study. BMJ Open, 11(9), e050185. https://doi.org/10.1136/bmjopen-2021-050185

What to Do When You Feel Short of Breath With COPD

You’re carrying laundry up the stairs. Halfway up, your chest tightens. Breathing feels shallow, effortful. You stop, grip the railing, wait for it to pass.

Or maybe it happens when you’re getting dressed in the morning, bending over to tie your shoes, or walking across a parking lot on a humid day.

If you live with chronic obstructive pulmonary disease (COPD), moments like these are familiar, and unsettling. The sensation of not being able to get enough air can trigger worry, frustration, and sometimes panic, which only makes breathing harder.

This article focuses on practical, everyday strategies for managing shortness of breath at home. Not quick fixes, but approaches that can help you feel more in control when breathing becomes difficult, and habits that may support easier breathing over time.


What Shortness of Breath Feels Like in COPD

Chronic obstructive pulmonary disease (COPD) is a long‑term lung condition that makes it harder to move air in and out of the lungs. It includes conditions like emphysema and chronic bronchitis, and it often causes ongoing shortness of breath that can worsen with activity or illness.

COPD affects the airways and air sacs in your lungs, making it harder for air to move in and out. Over time, this can cause breathlessness during activities that once felt routine.

People describe the sensation differently. Some feel tightness in the chest. Others experience what’s sometimes called “air hunger” — a feeling of not being able to take a satisfying breath. Fatigue often accompanies it, because breathing requires more effort than it should.

Symptoms can vary day to day, even hour to hour. Weather, activity level, sleep quality, stress, and exposure to irritants all play a role. A good morning doesn’t mean the afternoon will be easy, and a difficult day doesn’t necessarily signal that something has changed with your condition.

Understanding this variability can help reduce some of the anxiety that comes with unpredictable symptoms. Fluctuation is part of living with COPD, not necessarily a sign that things are getting worse.


Woman practicing pursed lip breathing while standing in her kitchen

What to Do in the Moment When Breathing Feels Difficult

When shortness of breath hits, having a few reliable strategies can help you regain a sense of control.

Pursed-Lip Breathing

This technique slows your breathing and helps keep airways open longer, making each breath more effective.

How to do it:

  • Breathe in slowly through your nose for about 2 seconds
  • Purse your lips as if you’re about to blow out a candle
  • Breathe out slowly and gently through your pursed lips for 4–6 seconds
  • Repeat until your breathing feels more controlled

Pursed-lip breathing works best when you practice it regularly, not just during episodes. The more familiar it becomes, the easier it is to use when you really need it.

Positioning Your Body

Certain positions can ease the work of breathing by giving your diaphragm more room to move.

  • Standing: Lean forward slightly with your hands resting on a table, counter, or your thighs
  • Sitting: Lean forward with your elbows on your knees or on a table in front of you
  • Resting: Lie on your side with pillows supporting your head and between your knees

Find what works for you. Different positions help different people, and what helps may vary depending on the situation.

Slow Down and Pause

When you feel breathless, the instinct is often to push through. But continuing activity can make symptoms worse.

Stop what you’re doing. Sit or lean if you can. Give your breathing time to settle before deciding whether to continue, modify, or rest.


Everyday Habits That Support Easier Breathing

Beyond in-the-moment strategies, certain daily habits can help reduce how often breathlessness disrupts your day.

Plan Activities to Conserve Energy

Pacing yourself matters. Break tasks into smaller steps with rest periods in between. Tackle more demanding activities earlier in the day when energy is often higher. Sit down for tasks when standing isn’t necessary.

This kind of planning is all about doing things in a way that works with your breathing, not against it.

Stay Consistent With Prescribed Therapy

If you use inhalers, nebulizers, or supplemental oxygen, using them as prescribed helps keep symptoms more stable. Skipping doses or using equipment inconsistently can make breathlessness harder to manage.

If you’re unsure whether your current therapy is working, or if you’re having trouble using your equipment correctly, talk with your care team. Small adjustments can sometimes make a meaningful difference.

Create a Comfortable Home Environment

Indoor air quality matters more than most people realize. Reducing dust, avoiding strong fragrances, and keeping humidity at a comfortable level can all help.

If outdoor air quality is poor, due to heat, humidity, pollen, or pollution, staying indoors with windows closed may help prevent symptom flares.

Know Your Triggers

Pay attention to what tends to make breathing harder for you. Common triggers include:

  • Extreme temperatures (hot or cold)
  • Strong odors, smoke, or fumes
  • Physical exertion without rest breaks
  • Respiratory infections
  • Stress or anxiety

You won’t be able to avoid every trigger, but awareness helps you prepare and respond more effectively.


Active senior man leaning against a tree trying to breathe while walking outdoors

When Shortness of Breath Is a Sign to Call for Help

Learning to manage symptoms at home is important, but so is recognizing when symptoms need clinical attention.

Consider reaching out to your care team if:

  • Breathlessness feels different from your usual baseline
  • Your usual strategies (breathing techniques, rest, medication) aren’t helping
  • You notice new symptoms alongside breathlessness, such as fever, chest pain, swelling, or changes in mucus color
  • You’re using your rescue inhaler more frequently than normal
  • Symptoms are interfering with sleep, eating, or basic daily activities

These don’t necessarily mean something serious is happening, but they’re worth a conversation. Early attention to changes can often prevent bigger problems.

If you experience severe shortness of breath, confusion, bluish lips or fingertips, or chest pain, seek emergency care immediately.


How Rotech Healthcare Supports Patients at Home

Managing COPD at home is easier when you have the right equipment, understand how to use it, and know who to call when questions come up.

Rotech Healthcare provides home respiratory equipment, including oxygen therapy, nebulizers, and CPAP/BiPAP devices, along with patient education and ongoing support. Our respiratory specialists help patients understand their therapy, troubleshoot equipment concerns, and stay connected to their care.

Programs like COPDBridge™ offer structured support during transitions from hospital to home, when patients are often most vulnerable to setbacks. And for those managing respiratory conditions long-term, CarePLUS™ provides continued monitoring and care coordination.

The focus is on helping you feel supported, informed, and more confident managing breathing at home.


Man with oxygen mask being put on face by doctor

COPD Shortness of Breath: Common Questions Answered

Why does shortness of breath come and go with COPD?

COPD symptoms can fluctuate based on activity, weather, air quality, sleep, stress, and overall health. A difficult morning doesn’t mean the rest of the day will be hard, and good days don’t mean the condition has improved. Day‑to‑day variability is a normal part of living with COPD.

Is it normal to feel tired after breathing feels difficult?

Breathing with COPD takes more effort than normal, which can lead to fatigue. Feeling worn out after episodes of breathlessness is common. Pacing activities and allowing time to recover can help conserve energy.

What breathing technique helps most with COPD breathlessness?

Pursed‑lip breathing is one of the most effective and widely recommended techniques. It helps slow breathing, keeps airways open longer, and reduces the sensation of air hunger. Practicing it regularly makes it easier to use when symptoms arise.

Should I use oxygen when I feel short of breath?

Only if your healthcare provider has prescribed supplemental oxygen for you. Oxygen therapy is based on specific oxygen levels and needs, and it should not be used “as needed” unless your care team has instructed you to do so.

How do I know when my symptoms are getting worse?

Pay attention to changes from your usual baseline. If breathlessness feels different, your normal strategies aren’t helping, or you notice new symptoms such as fever, increased mucus, or chest tightness, it’s a good idea to contact your care team.

Can anxiety make COPD breathlessness worse?

Yes. Anxiety can lead to faster, shallower breathing, which may intensify the feeling of breathlessness. This can create a cycle where breathing difficulty increases anxiety. Techniques like pursed‑lip breathing can help interrupt that cycle.

What position helps most when I’m short of breath?

Leaning forward, either standing with your hands on a surface or sitting with elbows on your knees, often helps by giving the diaphragm more room to work. The most helpful position can vary, so experimenting is important.

When should I go to the emergency room for shortness of breath?

Seek emergency care if you experience severe breathlessness that doesn’t improve, confusion, chest pain, bluish lips or fingertips, or any symptoms that feel alarming or unfamiliar. If something feels seriously wrong, trust your instincts and get help.


Breathing Easier Starts With Awareness

Living with COPD means adapting to a body that works differently than it used to. That’s frustrating, and some days are harder than others.

But breathlessness doesn’t have to mean helplessness. With practical techniques, thoughtful daily habits, and support from your care team, many people with COPD find ways to manage symptoms and maintain quality of life.

Pay attention to your body. Communicate with the people involved in your care. And know that small, consistent actions often matter more than dramatic interventions.

New to CPAP or BiPAP? How Rotech Helps You Get Started (And Stay on Track)

Getting diagnosed with sleep apnea can feel like a lot to process, especially when you’re handed a prescription for a CPAP or BiPAP machine and sent home to figure it out.

The questions start piling up fast:

  • “How am I supposed to sleep with a mask on my face?”
  • “What if I can’t get comfortable or I pull it off in my sleep?”
  • “Who helps me with insurance? Equipment? Follow-ups?”

These concerns are completely valid. For many patients, sleep therapy can feel overwhelming when follow‑up and education aren’t built into the process from the start.

At Rotech Healthcare, we approach things differently. Our goal isn’t just to deliver a machine. It’s to help you actually use it, get comfortable with it, and see the results that made your doctor prescribe it in the first place.

Through our Sleep Central education hub and SleepWELL™ compliance program, we work with thousands of patients across the country to simplify everything from referrals and insurance to mask fitting and long-term therapy support.


Why Starting CPAP or BiPAP Therapy Feels So Overwhelming

Let’s acknowledge the obvious: strapping a mask to your face and trying to sleep isn’t intuitive. Most people struggle at first, and that’s completely normal.

But beyond the physical adjustment, new patients often face a maze of logistical challenges:

  • Insurance and billing confusion. What’s covered? What isn’t? How do compliance requirements work?
  • Equipment decisions without guidance. There are dozens of mask styles and machine options. Without proper fitting, patients end up with equipment that leaks, pinches, or feels unbearable.
  • Lack of follow-up. Many suppliers treat CPAP like a one-time transaction. Once the box arrives, you’re on your own, googling troubleshooting tips at 2 a.m. when something goes wrong.
  • Unclear expectations. How long until therapy feels normal? What should you do if it’s not working? Who do you call?

This is exactly why so many people abandon CPAP therapy within the first few months. Studies consistently show that early support, real support, not just a phone number on a receipt, makes the difference between patients who stick with therapy and those who give up.


Woman sitting up in bed with a CPAP mask on giving a thumbs up and smiling

How Rotech Simplifies the Experience from Day One

Rotech isn’t a supplier that drops off a box and wishes you luck. We function as an extension of your care team, coordinating with your doctor, walking you through the process, and staying involved as you adjust to therapy.

Referrals and Coordination Without the Runaround

When your doctor refers you to Rotech, we take it from there. We handle coordination with your physician, communicate directly with you about next steps, and answer questions as they come up. No waiting for callbacks. No wondering what happens next.

We also provide patient and caregiver education materials designed to actually help, not generic pamphlets, but practical resources that address the specific concerns people have when starting sleep therapy.

Equipment Setup That Fits Your Life

CPAP and BiPAP aren’t one-size-fits-all. A machine that works perfectly for one patient might be completely wrong for another. Your face shape, sleep position, breathing patterns, and comfort preferences all matter.

Our setup process includes:

  • Machine selection based on your prescription and the features you need
  • Individualized mask fitting to minimize leaks and maximize comfort
  • Headgear adjustment so nothing pinches, pulls, or slides off overnight
  • Comfort accessory consultation for issues like dry mouth, nasal congestion, or skin irritation

This can happen virtually or in person at one of Rotech’s clinic locations — whatever works best for you.


Sleep Central: Your Hub for CPAP and BiPAP Success

Sleep Central is Rotech’s dedicated support hub for sleep therapy patients. Instead of hunting through random websites or hoping your insurance company can answer a technical question, you have one reliable resource for everything CPAP and BiPAP.

What’s available through Sleep Central:

  • Step-by-step equipment guides for setup and daily use
  • Information on different mask types and how to find the right fit
  • Cleaning and maintenance instructions to keep equipment working properly
  • Answers to the most common therapy questions

Whether you’re learning to use your machine for the first time or troubleshooting an issue six months in, Sleep Central gives you clear, practical information without the runaround.

And when you need a person, not a webpage: Sleep Central connects you with trained sleep therapy specialists by phone or online chat. Mask uncomfortable? Therapy not feeling right? Questions about your pressure settings? You can talk to someone who actually knows what they’re doing, and who will help you find a solution.


Man sleeping in bed with a CPAP mask on his face

SleepWELL™: Real Support During the Hardest Part

The first 90 days of CPAP or BiPAP therapy are make-or-break.

This is when you’re building new habits, adjusting to sleeping with a mask, and meeting the compliance requirements your insurance company sets. It’s also when most people quit, not because the therapy doesn’t work, but because they hit a wall and don’t have anyone to help them through it.

The SleepWELL™ program exists specifically to support you during this period.

What SleepWELL™ Provides

  • Regular check-ins from CPAP specialists — Proactive outreach, not just reactive support when you call with a problem
  • Therapy monitoring — Tracking your usage and effectiveness so issues get caught early
  • Early troubleshooting — Addressing comfort concerns, leaks, or equipment problems before they derail your progress
  • Compliance guidance — Helping you understand and meet insurance requirements within the 90-day window
  • Encouragement when you need it — Starting sleep therapy is hard. Having someone in your corner makes it easier.

Think of SleepWELL as your safety net during the adjustment period. Someone is paying attention. Someone is checking in. And someone will help you course-correct before small problems become reasons to give up.


Better Sleep Starts With Better Support

CPAP and BiPAP therapy can genuinely transform your health and bring you better sleep, more energy, reduced health risks, improved quality of life. But only if you stick with it long enough to see results.

Through Sleep Central and SleepWELL, Rotech provides the education, resources, and hands-on support that turn a medical device into a therapy that actually works for your life.

From your first questions about equipment to your 90-day compliance milestone and beyond, we’re here to help, not just as a supplier, but as a partner in your sleep health.

Ready to get started? Contact Rotech Healthcare or visit Sleep Central to learn more about CPAP and BiPAP support.


Woman holding up CPAP mask with confused look on her face

Frequently Asked Questions About CPAP and BiPAP Therapy

How long does it take to get used to CPAP or BiPAP?

Most people need 2-4 weeks to adjust to sleeping with a mask, though some adapt faster and others take longer. The key is consistent use, even on difficult nights, combined with proper mask fit and support. Patients who get help troubleshooting early issues tend to adapt more successfully than those trying to figure it out alone.

What if I can’t tolerate my CPAP mask?

Mask discomfort is one of the most common reasons people struggle with therapy, and it’s almost always fixable. The problem is usually fit, not the therapy itself. Rotech offers individualized mask fittings to find options that work for your face shape, sleep position, and breathing patterns. If one mask isn’t working, there are dozens of alternatives to try.

Does insurance cover CPAP and BiPAP equipment?

Most insurance plans, including Medicare, cover CPAP and BiPAP equipment for patients with a sleep apnea diagnosis. However, insurance often requires compliance documentation — proof that you’re using the machine regularly during the first 90 days. Rotech helps patients understand their coverage and navigate compliance requirements.

What happens if I don’t meet CPAP compliance requirements?

Insurance companies typically require patients to use CPAP for at least 4 hours per night for 70% of nights during the first 90 days to demonstrate medical necessity. If you don’t meet this threshold, your insurer may not cover the equipment long-term. The SleepWELL program helps patients track usage and troubleshoot problems early to stay on track with compliance.

Can I get help with CPAP if I have questions after setup?

Yes. Sleep Central provides ongoing support, not just at setup. You can access educational resources anytime, and trained sleep therapy specialists are available by phone or online chat to help with questions, troubleshooting, or concerns that come up weeks or months into therapy.

What’s the difference between CPAP and BiPAP?

CPAP (Continuous Positive Airway Pressure) delivers a single constant pressure throughout the night. BiPAP (Bilevel Positive Airway Pressure) delivers two pressure levels, higher when you inhale, lower when you exhale. BiPAP is often prescribed for patients who need higher pressures or have difficulty exhaling against constant pressure. Your doctor will prescribe the appropriate therapy based on your diagnosis and needs.

Why do so many people quit CPAP therapy?

Most people who quit do so within the first few months, usually because of mask discomfort, pressure adjustment issues, or feeling like they’re struggling without support. Early intervention and ongoing support significantly improve long-term adherence. That’s exactly why programs like SleepWELL exist: to help patients get through the adjustment period and experience the benefits of consistent therapy.

CPAP Adherence Rates Haven’t Improved Much. SleepWELL™ Addresses Why.

CPAP therapy remains the gold standard for treating obstructive sleep apnea (OSA). Prescribing it is straightforward. Getting patients to use it consistently, night after night, month after month, is an entirely different problem.

Most clinicians already know this. Non-adherence rates have remained stubbornly high for decades, even as devices have become quieter, smaller, and more comfortable. The 90-day compliance window required by payers creates urgency, but it doesn’t account for the behavioral realities of habit formation, the impact of early negative experiences, or the social determinants that shape whether someone actually uses their equipment.

The gap between “device delivered” and “therapy established” is where outcomes fall apart.

Rotech Healthcare’s SleepWELL™ Program was designed to close that gap — functioning as an extension of clinical care teams with structured monitoring, proactive outreach, and the kind of early-phase support that research consistently links to improved long-term adherence.


The Adherence Problem Isn’t About Devices Anymore

If better equipment solved the adherence problem, we’d have solved it by now. Modern CPAP machines are dramatically improved from a decade ago, with auto-adjusting pressures, integrated humidification, quieter motors, and sleeker profiles. Yet adherence rates have barely budged.

The issue is behavioral, not mechanical.

Clinicians are asking patients to adopt a new nightly routine involving unfamiliar equipment, physical discomfort, and a learning curve, all within a compressed timeline that determines insurance coverage. That’s a significant behavioral ask, and even minor friction points (mask discomfort, dry mouth, pressure intolerance) are enough to derail the process entirely.

Two factors compound the challenge:

The 90-day cliff. Payer compliance requirements create a high-stakes window where failure has lasting consequences. Patients who miss the threshold often lose coverage, which makes subsequent adherence even harder to achieve.

Clinical bandwidth limitations. Most care teams don’t have capacity for the kind of proactive, high-frequency outreach that early-phase PAP therapy requires. By the time a patient calls with a problem, if they call at all, the pattern of non-use may already be established.

Patients don’t just need equipment. They need a support structure that catches problems early, reinforces positive behavior, and keeps therapy on track during the critical adaptation period.


Healthcare professional in white coat instructing how to put CPAP mask on mannequin head to patient

How SleepWELL™ Serves as an Extension of Your Care Team

SleepWELL™ operates on a straightforward premise: patients do better when therapy is actively managed, especially during the first 90 days when drop-off risk peaks. 

The program addresses common failure points through a combination of monitoring, outreach, and clinical-grade support, an approach aligned with what adherence research consistently identifies as effective.

1. Monitoring That Enables Intervention

SleepWELL™ tracks usage data and generates compliance reports that include metrics like usage time, mask leak rates, and estimated AHI. This isn’t passive data collection, rather it’s designed to support a “manage by exception” model where concerning patterns trigger follow-up before they become therapy abandonment.

Remote monitoring frameworks are specifically cited in the literature as opportunities to improve real-world adherence, particularly when paired with behavioral support rather than surveillance alone.

2. Early-Phase Outreach When It Matters Most

One of the most consistent findings in adherence research: early experience shapes long-term behavior. Patients who struggle in the first few weeks are far more likely to abandon therapy entirely.

SleepWELL™ emphasizes proactive patient contact during the initial 90-day period, supported by real-time compliance measurement. This aligns with evidence showing that coaching and telemonitoring programs improve adherence, and that longer-duration support sustains improvements more effectively than brief interventions.

The goal is to catch small problems (mask fit issues, pressure discomfort, usage gaps) before they calcify into reasons to quit.

3. Clinical-Grade Support for a Complex Therapy

PAP adherence barriers are rarely one-dimensional. Patients often need both technical troubleshooting (equipment adjustments, interface changes) and motivational reinforcement (encouragement, problem-solving, realistic expectations) to persist through the adjustment period.

SleepWELL™ provides access to trained CPAP specialists and respiratory therapists, not just customer service representatives, who can address the clinical nuances of PAP therapy. That distinction matters when the conversation moves beyond “how do I turn this on” to “why does this feel wrong and should I keep trying.”

4. Resupply and Ongoing Follow-Up

PAP therapy isn’t a one-time setup. Mask cushions degrade, filters need replacement, fit changes over time, and life circumstances shift. Without ongoing attention, even initially adherent patients can drift into non-use.

SleepWELL™ includes structured resupply and continued follow-up designed to maintain compliance and support infection control, keeping therapy functional over the long term, not just through the initial compliance window.


What the Evidence Actually Supports

The adherence literature points consistently toward several principles:

  • Early intervention matters. Patients who receive intensive support in the first weeks of therapy show better long-term adherence than those who receive standard care.1
  • Monitoring alone isn’t enough. Data collection without response doesn’t move the needle. The value is in actionable monitoring — identifying problems and intervening promptly.
  • Behavioral support complements technical support. Adherence is a behavior change challenge, not just an equipment challenge. Programs that address motivation, troubleshooting, and reinforcement outperform those focused solely on device delivery.
  • Sustained support outperforms brief interventions. Short-term coaching programs produce short-term improvements. Durable adherence requires durable support structures.

SleepWELL™ was designed with these principles in mind, not as an equipment delivery service, but as a managed program that bridges the gap between prescription and sustained use.


Man sitting on bed stretching his arms with a CPAP mask on his face

A Practical Consideration for Referral Partners

For clinicians and care teams managing sleep apnea populations, the question isn’t whether adherence matters — it obviously does. The question is whether your current model addresses the behavioral and operational barriers that drive non-adherence.

If your patients are receiving equipment without structured follow-up, without proactive monitoring, without early-phase intervention, then the adherence gap is built into the process.

SleepWELL™ offers an alternative: a program designed to support patients through the highest-risk period, generate compliance data your team can act on, and function as a genuine extension of clinical care rather than a transactional equipment handoff.

To learn more about SleepWELL™ and how it supports PAP therapy outcomes, contact Rotech Healthcare.


Frequently Asked Questions: CPAP Adherence and SleepWELL™

What is considered CPAP adherence or compliance?

The most commonly used definition, particularly for insurance purposes, is the CMS standard: using CPAP for at least 4 hours per night on 70% of nights during the first 90 days of therapy. However, clinical benefit typically requires more consistent use; many guidelines recommend 6+ hours nightly for optimal outcomes. SleepWELL™ tracks usage data and supports patients in meeting both payer requirements and clinical goals.

Why do so many patients stop using CPAP?

Non-adherence is multifactorial. Common reasons include mask discomfort, pressure intolerance, nasal congestion or dryness, difficulty adjusting to the sensation of positive airway pressure, and lack of perceived benefit in the early weeks. The 90-day compliance window compounds these challenges by creating a high-stakes timeline that doesn’t align well with typical behavior change patterns.

Does remote monitoring improve CPAP adherence?

Evidence suggests that remote monitoring can improve adherence, but primarily when combined with active intervention rather than passive data collection. Programs that use monitoring data to trigger outreach and troubleshooting show better outcomes than those that simply track usage without response. SleepWELL™ is designed around this “monitor and respond” model.

What makes early-phase support so important for PAP therapy?

Research consistently shows that early experience with CPAP predicts long-term adherence.1 Patients who struggle in the first few weeks are significantly more likely to abandon therapy. Early-phase support, such as proactive check-ins, rapid troubleshooting, motivational reinforcement, addresses problems before they become entrenched patterns of non-use.

How does SleepWELL™ differ from standard equipment delivery?

Standard delivery models focus on getting devices to patients. SleepWELL™ is a managed program that includes proactive monitoring, compliance reporting, early-phase outreach, access to trained CPAP specialists and respiratory therapists, and ongoing resupply coordination. The program functions as an extension of clinical care teams rather than a transactional supplier relationship.

Can SleepWELL™ generate compliance reports for clinical teams?

Yes. SleepWELL™ provides compliance reports with metrics including usage time, mask leak data, and estimated AHI. These reports can support clinical decision-making and documentation requirements.

What types of patients benefit most from structured adherence support?

While all PAP patients benefit from support, structured programs like SleepWELL™ may be particularly valuable for patients with limited health literacy, those with complex comorbidities, patients without strong caregiver support, and those who express ambivalence or anxiety about starting therapy. These populations face higher drop-off risk and often benefit most from proactive intervention.


References

  1. Dielesen, J., Ledwaba-Chapman, L. J., Kasetti, P., Husain, N. F., Skinner, T. C., Pengo, M. F., Whiteman, T., Asimakopoulou, K., Merritt, S., Jones, D., Dickel, P., Pulakal, S., Ward, N. R., Pepperell, J., Steier, J., & Sathyapala, S. A. (2025). Six early CPAP-usage behavioural patterns determine peak CPAP adherence and permit tailored intervention, in patients with obstructive sleep apnoea. Thorax, 80(5), thorax-2024-221763. https://doi.org/10.1136/thorax-2024-221763

What Makes a Successful Home NIV Transition? A Practical Guide for Discharge Teams

Home care is becoming an increasingly desirable and prevalent option for patients with chronic respiratory conditions. For patients requiring non-invasive ventilation (NIV), the hospital-to-home transition represents a high-risk inflection point, one where even technically correct discharge orders can fail to translate into effective therapy establishment.

The data underscores this vulnerability. Among patients hospitalized with hypercapnic respiratory failure due to COPD, approximately 40% are rehospitalized within 30 days.1 The highest risk for rehospitalization occurs within the first two days after discharge.1 For patients transitioning to home NIV, outcomes depend heavily on factors that extend well beyond the prescription itself: patient selection, caregiver readiness, equipment delivery timing, education quality, and, critically, structured follow-up.

Research demonstrates that unsupervised patients transitioning to home NIV have significantly worse prognoses compared to those receiving structured follow-up (HR 2.54, 95% CI 1.48–4.33).2 This finding reinforces what discharge teams already know intuitively: equipment delivery alone does not constitute therapy establishment.

For discharge teams seeking to optimize NIV transitions, the evidence points to a structured, multidisciplinary approach, exactly the model that Rotech Healthcare’s NIVnow™ program was designed to deliver.


Why NIV Home Transitions Fail, Even When the Orders Are Correct

The clinical literature on NIV transitions identifies several recurring failure modes, many of which are invisible in the inpatient setting:

Patient and caregiver factors:

  • Insufficient education on device operation, interface management, and alarm response
  • Unrealistic expectations about symptom improvement timeline
  • Inadequate caregiver support during the critical early adaptation period
  • Poor health literacy or cognitive barriers to self-management

System and process factors:

  • Discharge timing that precludes adequate education and setup
  • Lack of coordination between inpatient teams and home equipment providers
  • Absence of structured follow-up pathways
  • “Last-day scramble” discharge processes that compress education into inadequate timeframes

Environmental factors:

  • Home readiness issues (power reliability, equipment placement, emergency planning)
  • Supply chain gaps that leave patients without necessary interfaces or accessories
  • Geographic or socioeconomic barriers to follow-up care

A cohort study evaluating outcomes in hypercapnic patients transitioning to home NIV found that failure to attend NIV follow-up was associated with significantly worse outcomes.2 This suggests that the transition process itself, not merely the clinical indication or device prescription, is a critical determinant of success.

The implication for discharge teams is clear: successful NIV transition requires treating the discharge as the beginning of a care process, not the conclusion of an inpatient episode.


Healthcare professional writing with pen on discharge paperwork with telephone and stethoscope in background

The Five Pillars of Successful Home NIV Transitions

Five elements emerge as “must-have” components of effective NIV discharge planning. Each addresses a common failure mode and aligns with the structured approach that programs like NIVnow™ are designed to support.

Pillar 1: The Right Patient at the Right Time

A successful transition begins with clarity on indication and stability. The inpatient team’s role extends beyond prescribing; it encompasses ensuring that NIV is appropriate for the specific patient and that the patient is positioned to succeed at home.

Literature on hospital-to-home NIV transitions emphasizes the importance of patient selection and the particular vulnerability of the immediate post-discharge period.1 Patients with persistent hypercapnia (PaCO₂ > 52 mm Hg) after stabilization from acute exacerbation may benefit from NIV initiation, but timing and readiness assessment remain critical.3

Practical discharge-team prompts:

  • Is the patient clinically stable enough for home NIV initiation?
  • Is there a clear plan for outpatient or home-based follow-up?
  • Are treatment goals and realistic expectations aligned with the patient (symptom relief, improved gas exchange, sleep quality, reduced exacerbations)?
  • Has the patient demonstrated adequate tolerance during inpatient NIV acclimation?

Pillar 2: Discharge Planning Begins Early, Before Discharge Is Imminent

Transitions work best when planning begins during the inpatient stay and involves multiple stakeholders. Reviews of long-term NIV transitions emphasize multidisciplinary collaboration, patients, caregivers, hospital teams, and equipment providers, because no single role covers the entire care pathway.4

A practical framework: If NIV is being considered, treat it as a care pathway rather than a line item on the discharge order set. This shift in framing reduces “last-day scramble” problems that patients experience immediately upon arriving home.

Early discharge planning allows for:

  • Adequate time for patient and caregiver education
  • Equipment provider coordination and home assessment
  • Identification of potential barriers (power reliability, caregiver availability, transportation)
  • Interface trials and comfort optimization before discharge

Pillar 3: Education That Goes Beyond a Pamphlet

Patient education is a well-established predictor of therapy adherence and post-discharge outcomes.5 For NIV specifically, evidence on hospital-to-community transitions identifies training and support for patients and families as a core need, particularly during the first 30 days.6

Single-dose education administered at discharge is associated with minimal impact on readmission rates; multicomponent, reinforced education demonstrates more consistent benefit.7

What effective NIV education covers:

Education Domain Key Content Areas
Device operation Power-on/off, basic settings awareness, travel considerations
Interface management Mask/interface application, fit optimization, leak minimization, skin protection strategies
Maintenance Cleaning protocols, supply replacement schedule, infection control basics
Alarm response Common alarms, troubleshooting steps, criteria for urgent evaluation vs. provider contact
Expected trajectory Realistic timeline for symptom improvement (sleep, energy, dyspnea), when to report changes

The goal is not merely information transfer but competency development, ensuring patients and caregivers can problem-solve common issues independently while knowing when and how to escalate concerns.

Pillar 4: Home Readiness and Device/Interface Matching

Home NIV succeeds when it fits real life. Transitions literature notes the need for coordinated human and technical resources, highlighting the importance of continued monitoring and logistics in the home setting.8

Home readiness assessment checklist:

Domain Assessment Questions
Power and environment Is there reliable electrical access? Does the patient need guidance on backup power or contingency planning?
Caregiver support Is caregiver support available when needed, especially during the early adaptation period?
Supplies and interfaces Are supplies and interface options available to address comfort issues quickly? Are backup interfaces accessible?
Emergency planning Does the patient have a clear understanding of when to seek urgent care vs. contact the equipment provider?
Follow-up logistics Can the patient access follow-up appointments (in-person or telehealth)? Are transportation barriers addressed?

Standardizing home readiness assessment as part of discharge workflow reduces variability and ensures critical factors are not overlooked during time-pressured discharges.

Pillar 5: A Structured Follow-Up Plan with Accountability

This is the most frequently missing component in NIV transitions, and potentially the most consequential.

In a cohort study of patients transitioned to home NIV after hypercapnic hospitalization, failure to attend NIV follow-up was associated with significantly worse outcomes.2 Follow-up is not a “nice to have”; it is a clinical necessity during the highest-risk post-discharge window.

Elements of effective follow-up structure:

  • Scheduled early check-ins: Proactive contact within the first week, not only “call us if you need us”
  • Defined escalation pathways: Clear protocols for adherence challenges, symptom changes, or equipment problems
  • Accountable ownership: Designated responsibility for follow-up (equipment provider, home health, clinic) with documented handoff
  • Remote monitoring integration: Where available, use of device data downloads to identify adherence or efficacy concerns early

Research on multicomponent readmission-reduction interventions consistently demonstrates that the effect of interventions is related to the number of components implemented, whereas single-component interventions are unlikely to reduce readmissions significantly.9


Two female healthcare professionals wearing scrubs and stethoscopes looking at tablet together and smiling

How NIVnow™ Supports Successful Hospital-to-Home NIV Transitions

Rotech Healthcare developed NIVnow™ specifically to support patients on home NIV with a multifaceted approach, the same model that the research base repeatedly identifies as beneficial during transitions of care.

1. Individualized Plans of Care

NIVnow™ includes individualized plans of care that help standardize post-discharge expectations across care team members. This is particularly valuable when multiple providers touch the patient’s care journey, reducing variability and ensuring continuity.

2. Patient and Caregiver Education That’s Designed to Stick

NIVnow™ emphasizes hands-on patient and caregiver education, reinforcing the type of competency-based training that transition research highlights as essential for success. Education extends beyond discharge, with reinforcement during follow-up contacts.

3. Compliance Coaching and Therapy Support

The program provides customized ventilator therapy compliance coaching using technology and trained professionals to support therapy establishment, not just initiation. Comfort drives adherence, and NIVnow™ addresses comfort barriers proactively.

4. Ongoing In-Home Follow-Ups with Respiratory Clinicians

NIVnow™ includes ongoing in-home follow-ups with respiratory clinicians, with regularly scheduled and as-needed visits. This approach aligns with evidence demonstrating that follow-up and continuity reduce risk during the post-discharge period.10

5. 24/7 Support Through Ventilator Case Managers

A frequent discharge-team concern is the “after-hours” gap — the 2 a.m. alarm that generates a frantic call with no clear pathway for resolution. NIVnow™ addresses this with a dedicated hotline for 24/7 clinical support, staffed by specially trained Ventilator Case Managers who provide ongoing assistance.

For discharge teams, NIVnow™ addresses the common causes of therapy breakdown: education gaps, comfort issues, and lack of follow-up structure, during the highest-risk window after discharge.


Summary: Home NIV Transition as a Care Process, Not a Transaction

For discharge teams aiming to reduce readmissions and improve long-term outcomes, home non-invasive ventilation must be supported as a clinical therapy, with education, coaching, follow-up, and clear escalation pathways, rather than treated as “equipment arranged.”

The value of multidisciplinary coordination and post-discharge support cannot be overstated. NIVnow™ is designed to deliver exactly that continuity, bridging the gap between inpatient care and sustainable home therapy.

For discharge teams, the value proposition is straightforward: fewer avoidable gaps, clearer handoffs, and patients who can establish effective NIV therapy at home, rather than returning to the hospital within days or weeks.

Contact Rotech Healthcare to learn more about NIVnow™ and how the program can support your NIV discharge planning.


Two healthcare professionals walking and smiling

Frequently Asked Questions: Home NIV Transitions

What is the most critical factor in successful home NIV transitions?

Structured follow-up is the most frequently missing — and most consequential — component. Research demonstrates that unsupervised patients transitioning to home NIV have significantly worse outcomes compared to those with structured follow-up programs (HR 2.54).2 Single-component interventions (such as equipment delivery alone) are unlikely to reduce readmissions; multicomponent approaches that include education, coaching, and follow-up show consistent benefit.

When should discharge planning for home NIV begin?

Discharge planning should begin during the inpatient stay, well before discharge is imminent. Early planning allows adequate time for patient education, caregiver training, equipment provider coordination, home readiness assessment, and interface optimization. Treating NIV discharge as a care pathway rather than a discharge-day line item reduces common “last-day scramble” failures.

What does effective NIV patient education include?

Effective education extends beyond pamphlets to include hands-on competency development. Key domains include device operation, interface application and comfort strategies, maintenance and infection control, alarm response and troubleshooting, and realistic expectations about symptom improvement timelines. Education should be reinforced during follow-up, not delivered only at discharge.

How does NIVnow™ differ from standard equipment delivery?

NIVnow™ provides a structured, multidisciplinary program rather than transactional equipment delivery. The program includes individualized care plans, hands-on patient and caregiver education, compliance coaching, ongoing in-home follow-ups with respiratory clinicians, and 24/7 access to specially trained Ventilator Case Managers. This approach addresses the education gaps, comfort issues, and lack of follow-up structure that commonly cause therapy breakdown.

What outcomes does home NIV therapy support when successfully established?

Research demonstrates that home NIV in appropriately selected patients can reduce 1-year mortality (from 33% to 10% in one RCT),1 decrease rehospitalization or death within 1 year (from 80.4% to 63.4%),1 and improve health-related quality of life, dyspnea, gas exchange, and exercise tolerance, with benefits increasing over time.

How should discharge teams assess home readiness for NIV?

Home readiness assessment should address power reliability and backup planning, caregiver availability (especially during early adaptation), supply and interface accessibility, emergency planning clarity, and follow-up logistics. Standardizing this assessment within discharge workflow reduces variability and ensures critical factors are not overlooked.


References

  1. Fortis, S. (2024). Why Home-NIV Should Begin in the Hospital, Not at Home. American Journal of Respiratory and Critical Care Medicine, 210(3), 260–261. https://doi.org/10.1164/rccm.202401-0214vp
  2. Fox, B. D., Bondarenco, M., Shpirer, I., Natif, N., & Perl, S. (2022). Transitioning from hospital to home with non-invasive ventilation: who benefits? Results of a cohort study. BMJ Open Respiratory Research, 9(1), e001267. https://doi.org/10.1136/bmjresp-2022-001267
  3. Jen, R., Ellis, C., Kaminska, M., Road, J., & Najib Ayas. (2023). Noninvasive Home Mechanical Ventilation for Stable Hypercapnic COPD: A Clinical Respiratory Review from Canadian Perspectives. Canadian Respiratory Journal, 2023, 1–7. https://doi.org/10.1155/2023/8691539
  4. Xiao, L., Amin, R., & Nonoyama, M. (2023). Long-term mechanical ventilation and transitions in care: A narrative review. Chronic Respiratory Disease, 20, 147997312311763-147997312311763. https://doi.org/10.1177/14799731231176301
  5. Hansen, L. O., Young, R. S., Hinami, K., Leung, A., & Williams, M. V. (2011). Interventions to Reduce 30-Day Rehospitalization: A Systematic Review. Annals of Internal Medicine, 155(8), 520. https://doi.org/10.7326/0003-4819-155-8-201110180-00008
  6. Fernando, Gaio, M., Óscar Ramos Ferreira, Oliveira, C., Pedreira, L., & Cristina Lavareda Baixinho. (2024). Nursing Interventions for Client and Family Training in the Proper Use of Noninvasive Ventilation in the Transition from Hospital to Community: A Scoping Review. Healthcare, 12(5), 545–545. https://doi.org/10.3390/healthcare12050545
  7. Barrett, J. B., Trambley, A., Blessinger, E. K., Sexton, M. M., Lupica, M., Hasselblad, M., Cunningham, K. E., Kripalani, S., & Choma, N. N. (2025). Reduced Hospital Readmissions Through Personalized Care: Implementation of a Patient, Risk-Focused Hospital-Wide Discharge Care Center. NEJM Catalyst, 6(6). https://doi.org/10.1056/cat.24.0420
  8. Levey, C., Manthe, M., Taylor, A., Sahibqran, M., Walker, E., McDowell, G., Livingston, E., Benjafield, A. V., & Carlin, C. (2024). Impact of remote-monitored home non-invasive ventilation on patient outcomes: a retrospective cohort study. MedRxiv (Cold Spring Harbor Laboratory). https://doi.org/10.1101/2024.04.11.24305702
  9. Kripalani, S., Theobald, C. N., Anctil, B., & Vasilevskis, E. E. (2020). Reducing hospital readmission rates: Current strategies and future directions. Annual Review of Medicine, 65(1), 471–485. https://doi.org/10.1146/annurev-med-022613-090415
  10. Sharma, S., Stansbury, R., Mayuri Mudgal, Srinivasan, P., Rojas, E., Olgers, K. K., Knollinger, S., Selim, B. J., & Wen, S. (2025). Post-Discharge non-invasive ventilation for hypercapnic respiratory failure: Outcomes in a Rural Cohort. PLoS ONE, 20(4), e0321420–e0321420. https://doi.org/10.1371/journal.pone.0321420

Managing Both COPD and Heart Failure? What You Need to Know

Living with one chronic condition is hard enough. Managing two that affect both your breathing and your heart can add another layer of complexity to everyday life.

COPD (chronic obstructive pulmonary disease) and heart failure often occur together, and the overlap can make symptoms harder to recognize and manage. Research shows that up to one-third of people with heart failure also have COPD,1 and when these conditions coexist, they can intensify each other in ways that aren’t always obvious.

With a clear understanding of how COPD and heart failure interact, and a care plan designed to address both, it’s possible to manage symptoms at home and reduce unexpected hospital visits.

At Rotech Healthcare, we specialize in helping patients living with COPD and heart failure get the equipment, education, and ongoing support they need to stay healthier and out of the hospital. This article will help you understand how these conditions are connected, what symptoms to watch for, and how we can help you take control of your care.


Why COPD and Heart Failure Often Go Together

If you have COPD and heart failure, you might wonder: why me? Why both? The truth is, these two conditions share so many risk factors and pathways that having one significantly increases your risk of developing the other. This isn’t bad luck — it’s biology.

Shared Risk Factors

COPD and heart failure often develop from the same underlying causes:2

Risk Factor How It Affects You
Smoking history Damages both lung tissue and blood vessels, contributing to both conditions
Aging Natural decline in heart and lung function increases vulnerability
Chronic inflammation Ongoing inflammation throughout the body affects both the heart and lungs
Sedentary lifestyle Reduced physical activity weakens both cardiovascular and respiratory systems
Air pollution and environmental exposures Long-term exposure damages lung tissue and promotes cardiovascular disease

How Each Condition Makes the Other Worse

COPD and heart failure create a cycle that can be difficult to break:

COPD puts extra strain on your heart. When your lungs don’t work efficiently, your body has to work harder to get enough oxygen. This extra effort strains the heart over time, potentially leading to heart failure, especially affecting the right side of the heart.

Heart failure makes breathing harder. When your heart can’t pump effectively, fluid can build up in your lungs. This fluid makes it even harder to breathe, worsening the symptoms you already experience from COPD.

The result is that each condition accelerates the progression of the other, which is why managing both together, rather than treating them separately, is so important.


Sporty senior man walking outdoors with headphones on and coughing, out of breath

Recognizing Symptoms When You Have Both Conditions

One of the most frustrating aspects of living with COPD and heart failure is that the symptoms overlap so much. It can be genuinely difficult to know which condition is causing your discomfort on any given day.

Symptoms Common to Both Conditions

  • Shortness of breath — especially during activity or when lying flat
  • Fatigue and low energy — feeling exhausted even after rest
  • Swelling in legs, ankles, or feet — more common with heart failure, but can occur with both
  • Difficulty sleeping — particularly when lying down
  • Reduced ability to exercise — getting winded more easily than before
  • Coughing — may be dry or produce mucus

Why Tracking Matters

Because these symptoms overlap, it’s critical to monitor changes rather than guess at the cause. A symptom that’s “normal” for your COPD might actually signal worsening heart failure, or vice versa.

This is exactly why working with a provider who understands both conditions makes such a difference. Tracking your symptoms over time helps you and your care team identify patterns, catch problems early, and adjust your treatment before small issues become emergencies.


How Rotech Supports Patients with COPD and Heart Failure with COPDBridge™

Managing two complex conditions at home requires more than just equipment delivery. It requires education, regular monitoring, and a care team that stays connected with you over time.

At Rotech Healthcare, we’ve built programs specifically designed to help patients like you manage their conditions at home, reducing hospitalizations and improving quality of life.

COPDBridge™: Intensive Support in the Critical First 30 Days

The weeks immediately following a hospital discharge are the most vulnerable time for COPD patients. Research shows that more than 20% of patients hospitalized for COPD are readmitted within 30 days.3 That’s why we created COPDBridge™.

COPDBridge™ is a comprehensive 30-day program designed to help you transition safely from hospital to home and stay out of the hospital.

What’s included:

  • Weekly visits with a respiratory therapist — including physical assessments, nutrition support, medication review, and smoking cessation resources if applicable
  • Daily monitoring and data collection — tracking your condition so changes are caught early
  • COPDBridge 30-Day Journal — a structured way to record your symptoms, track your progress, and identify patterns
  • Online patient education — accessible from any device, so you can learn at your own pace
  • Follow-up documentation — sent directly to your hospital and physician, keeping your entire care team informed

The goal: Help you recognize the early signs of an exacerbation, follow your COPD action plan, and get treatment before things get worse.

CarePLUS™: Ongoing Support Beyond the First 30 Days

While COPDBridge focuses on the critical post-discharge period, CarePLUS™ ensures you have everything you need for long-term success at home.

CarePLUS™ provides:

  • Overnight oximetry testing — monitoring your oxygen levels while you sleep to catch problems that daytime measurements miss
  • Home medical equipment — including hospital beds, wheelchairs, ventilators, oxygen supplies, and other equipment tailored to your needs
  • Care coordination — our team keeps your physicians and care team informed about how you’re doing at home
  • Ongoing troubleshooting and support — care coordinators available to answer questions, solve problems, and ensure your equipment is working properly

Think of CarePLUS as an extension of your care team — eyes and ears in your home that help catch issues before they become emergencies.

Learn More About CarePLUS™


Older man taking his medication at home as prescribed

Practical Tips for Managing Both Conditions at Home

While professional support is essential, there’s also a lot you can do every day to manage COPD and heart failure together.

Monitor Your Symptoms Daily

Pay attention to changes in your breathing, energy levels, and swelling. Keep a simple log, even just a few notes each day can help you spot patterns and give your care team valuable information.

Watch for warning signs that need attention:

  • Sudden increase in shortness of breath
  • New or worsening swelling in legs or ankles
  • Rapid weight gain (more than 2-3 pounds in a day or 5 pounds in a week)
  • Increased coughing or change in mucus color
  • Feeling unusually tired or confused

Take Medications as Prescribed

Both COPD and heart failure often require multiple medications. Take them exactly as prescribed, and don’t stop or change doses without talking to your doctor first. If you’re having trouble keeping track, ask your pharmacist about pill organizers or medication management tools.

Stay as Active as Safely Possible

It might seem counterintuitive when breathing is difficult, but gentle, regular physical activity can strengthen both your heart and lungs over time. Talk to your doctor about what level of activity is safe for you, and consider pulmonary rehabilitation if it’s available in your area.

Follow Dietary Guidelines

Both conditions benefit from limiting sodium intake, which can reduce fluid retention and ease the strain on your heart and lungs. Your care team can provide specific guidance based on your situation.

Don’t Skip Follow-Up Appointments

Regular check-ins with your doctors allow them to catch changes early and adjust your treatment plan as needed. If getting to appointments is difficult, ask about telehealth options or whether your home health provider can help coordinate care.


Man with supplemental oxygen on flexing outdoors in the woods

Remember, You’re Not Managing This Alone

Managing COPD and heart failure is challenging, but doable, especially when you partner with the right provider. It’s important to be proactive with your care, and be your own advocate. Rotech is here to help with our COPDBridge and CarePLUS programs, which focus on improving outcomes and making sure you have the equipment you need at home to manage your conditions. Contact us to learn more about how we can help you.


Frequently Asked Questions About COPD and Heart Failure

Why do COPD and heart failure often occur together?

COPD and heart failure share many risk factors, including smoking, aging, and chronic inflammation. Additionally, COPD puts extra strain on the heart over time because the body works harder to get enough oxygen. Heart failure, in turn, can cause fluid buildup in the lungs, worsening breathing problems. This creates a cycle where each condition accelerates the other.

How common is it to have both COPD and heart failure?

Very common. Research indicates that up to 30-40% of patients with heart failure also have COPD,1 and vice versa. Having both conditions together is associated with worse outcomes and more frequent hospitalizations, which is why coordinated management is so important.

How can I tell which condition is causing my symptoms?

This is one of the most challenging aspects of living with both conditions, since symptoms like shortness of breath, fatigue, and swelling occur with both COPD and heart failure. Tracking your symptoms daily helps identify patterns. Working with a provider like Rotech, who can monitor your oxygen levels and coordinate with your care team, makes it easier to determine what’s happening and respond appropriately.

What is the COPDBridge™ program?

COPDBridge™ is Rotech’s 30-day intensive support program for COPD patients transitioning from hospital to home. It includes weekly respiratory therapist visits, daily monitoring, patient education, a symptom-tracking journal, and direct communication with your care team. The goal is to reduce hospital readmissions by helping you catch problems early and manage your condition effectively at home.

What is CarePLUS™ and how does it help?

CarePLUS™ is Rotech’s ongoing support program that extends beyond the first 30 days. It includes overnight oximetry testing, home medical equipment supply, care coordination with your physicians, and responsive support from care coordinators. CarePLUS acts as an extension of your care team, helping identify issues before they become emergencies.

Can both conditions be managed at home?

Yes. With proper equipment, education, monitoring, and support, most patients with COPD and heart failure can manage their conditions at home. The key is having a comprehensive care plan and working with a provider who understands both conditions and can coordinate your care effectively.

What symptoms should I report to my doctor immediately?

Contact your care team or seek medical attention if you experience sudden worsening of shortness of breath, rapid weight gain (more than 2-3 pounds in a day), new or increased swelling, chest pain, confusion, or symptoms that don’t respond to your usual treatments. Early intervention can often prevent hospitalization.

Does insurance cover home respiratory therapy programs?

Most insurance plans, including Medicare, cover home respiratory equipment and related services for patients with qualifying diagnoses. Rotech works with most major insurance providers and can help you understand your coverage options.


References

  1. Axson, E. L., Sundaram, V., Bloom, C. I., Bottle, A., Cowie, M. R., & Quint, J. K. (2018). Hospitalisation and mortality outcomes of patients with comorbid COPD and heart failure: a systematic review protocol. BMJ Open, 8(6), e023058. https://doi.org/10.1136/bmjopen-2018-023058
  2. de Miguel-Díez, J., Chancafe Morgan, J., & Jimenez-Garcia, R. (2013). The association between COPD and heart failure risk: A review. International Journal of Chronic Obstructive Pulmonary Disease, 8, 305. https://doi.org/10.2147/copd.s31236
  3. Fortis, S. (2024). Why Home-NIV Should Begin in the Hospital, Not at Home. American Journal of Respiratory and Critical Care Medicine, 210(3), 260–261. https://doi.org/10.1164/rccm.202401-0214vp